Category: All

  • I’ve been to rehab four times and I may never stay sober. I’m still recovering.

    I’ve been to rehab four times and I may never stay sober. I’m still recovering.

    “It’s simple, hun—you have the disease.” Bill says this as he hands me a wooden chip inscribed with the serenity prayer:

    “God, grant me the serenity to accept the things I cannot change, the courage to change the things I can, and the wisdom to know the difference.”

    An biker who somehow landed in Westbank, Kelowna, Tom is paternal. I’ve never been told that I have a disease, but his words incite relief. I cannot stop drinking, and illness is better than badness. I have done horrible things.

    I accept a tattered copy of the Big Book and devour it, highlighting, underlining, and earmarking earnestly until I have it memorized. I meet others who do the same. We form unexpected kinships, our lives irrevocably intertwined through a singular, obstinate pursuit of wellness. I repent. They hold me. I have never felt such intimacy.

    When I leave 28 days later, we promise to stay in touch. I never speak to them again.

    I am 18 years old.

    I have been sober for 45 days, and something is very wrong. My legs have stopped working, and when I try to articulate how physically enervated I am—how utterly incapacitated—my councillors tell me to pray.

    “God, grant me the serenity to accept the things I cannot change, the courage to change the things I can, and the wisdom to know the difference.”

    I am drowning in a vast, violent emptiness. Anhedonia. Near-catatonia. The obsessions, the compulsions, the counting, the rituals; these I must relinquish to a Higher Power (though without them, I’m not sure who I am).

    “Stop thinking so much.”

    “You need humility.”

    I eat 1175 calories a day—no more, no less. Identical meals at breakfast, lunch, and dinner. To deviate would trigger a binge. Pleasure is not safe. I attend group sessions and while other women weep, I try to stay awake.

    Am I a sociopath?

    All I want is chocolate.

    I am 19 years old.

    I arrive with a black eye and hematoma on my chin. It obscures my jawline and deforms my cheekbones, my reflection as grotesque as the memories I suppress. I don’t know how it (I) got there.

    “Third time’s the charm.”

    I am too tired to have hope. After nearly three years of homelessness, I am also too tired not to. Alcohol and bulimia have been replaced by crack cocaine. I no longer feel human. The things I did at 18 pale by way of comparison.

    “Your brain is broken.”

    I am hostile. My mind is a rabid animal, and I don’t trust this place—these people—to tame it. One month becomes two. Two becomes three, then six, then seven. Something shifts. I listen in a way I never have before. I believe in a way I never have before. The obsessions, rituals, counting, compulsions; they haven’t left, but they have transmogrified into something like spirituality.

    “I could drink.”

    I stop what I am doing.

    Fall to my knees.

    Pray.

    “God, grant me the serenity to accept the things I cannot change, the courage to change the things I can, and the wisdom to know the difference.”

    Once. Twice. Three times.

    Six if the thought returns. Nine times. Twelve. Fifteen.

    I am terrified of myself.

    “Every moment you spend in treatment, your disease is outside doing push-ups in the parking lot. It gets stronger as you do. It will never go away.”

    In my sixth month I enrol in two university courses. One of them is introductory sociology. I am intrigued.

    The councillors become trusted confidantes. They convince me I can leave. They expect to see me regularly.

    I move into a basement apartment two blocks away. I visit the councillors every day, sometimes once, sometimes twice or more. I relay my academic successes.

    “Don’t let it go to your head. Recovery must come first.”

    I am 22 years old.

    “Fuck you!”

    The voice is not my own. A new woman has just arrived, and she is detoxing—hard. I am five months sober, and I have entered treatment voluntarily. I may return to my PhD, but I know I’m not prepared. I was promised that staff were trauma-informed.

    That was bullshit.

    Publicly funded, there are two councillors for thirty patients. Most have been street-entrenched for years or decades. We are told not to discuss drug use. Or violence. Or sex work. Or poverty.

    “If you get triggered, we don’t have the tools to contain you.”

    Twelve-step meetings are optional. AA members come bi-weekly to share their experience, strength, and hope. When they do, I look away.

    “God, grant me the serenity.” —

    I walk past the door, my fists clenched tightly. Bile rises in my throat.

    I see myself in them. I will see myself in them when a month, two months, a year, from now they use again. They will hate themselves. It will not be their fault.

    “This place is a joke!”

    This time the voice is mine. I am with the psychiatrist. I denigrate her profession.

    “I do not consent to being pathologized.”

    She raises her eyebrows; takes notes; says nothing.

    I leave early. In addition to bipolar disorder, obsessive compulsive disorder, borderline personality disorder, possible dissociative identity disorder, complex post-traumatic-stress disorder, somatoform pain disorder, possible autism, and, of course, severe alcohol and stimulant use disorders, my discharge summary notes that I present as rather angry.

    I am 30 years old.

    As I write this, I am 31 years old. I have been abstinent from alcohol and illicit drugs for nearly two years. Before my last relapse, I had been abstinent for eleven months. Prior to that (and prior to the two-year bender that was my Masters’ degree), I hadn’t touched drugs or alcohol for well over five years.

    My adult life has been shaped by substance use (or lack thereof): freneticism during periods of active use; temporal boundaries demarcated by surges of euphoria and devastating loss; rigidity and suffocation while sober; crystalline awareness that despite my Herculean efforts to think, look, and act normal, the best I’ll do is pass.

    Panic, regardless. I fully expect to use again. Perhaps not immediately but eventually, definitely.

    I am still recovering.

    Only now, I don’t say that I’m recovering from addiction. Alcohol and drug use were never the problems. In a society that was built on oppression, though (that is, in a society that wouldn’t exist without the ongoing displacement, dispossession, and disappearance of Indigenous peoples; that has been designed to control, regulate, and disadvantage Black communities; that approaches disability as a fatal character flaw; that produces enormous wealth disparities and prohibits anyone who can’t or won’t conform to White, cis-hetero patriarchal standards of productivity from access to power or resources), alcohol and drugs are convenient red herrings.

    I am still recovering.

    Rather than focus on recovering from a “hopeless state of mind and body,” however, I have turned my efforts outward.

    For someone who once espoused the merits of sobriety (and who viewed sobriety as the pinnacle of addict achievement), to now be unbothered by the idea of substance use (mine and anyone else’s) is a radical departure.

    How did I get here?

    During my third round of addiction treatment, I found sociology. I had very few expectations, but “the systematic study of society” seemed interesting, and it also fit my schedule. I still lived in extended care at treatment centre three, so I took the bus to campus between morning check-in, individual and group therapy sessions, and my daily chore routine. I wrote my first essays in the communal kitchen I shared with 120 other patients, and I asked staff to proofread my work because I didn’t own a computer (not that I would have been permitted to use one even if I had).

    At first, education was jarring. After four years immersed in twelve-step programs, to be introduced to the social determinants of health (that is, the socio-cultural, economic, and political conditions that positively or negatively influence one’s health status) was de-stabilizing. Specifically, the insight that exclusion on the bases of income, race, sex, gender, and disability, among other facets of one’s identity, is correlated with outcomes such as substance use confounded me. I had been taught that addiction was solely my responsibility. It was the product of a malignant mind, nothing more, and so extraneous conditions such as homelessness were consequences of one’s usage, not causes.

    The more I reflected, however, the more sociology made sense. I developed an “awareness of the relationship between personal experience and the wider society,”1 and was able to understand patterned behavior responses among social groups as they pertained to rates of addiction.

    Indigenous peoples, for example, report much higher rates of alcohol and illicit drug addiction than other ethnic groups. Why? Because White frontiersmen introduced alcohol as a tool of colonization. Not only was it a profitable trade good, but authorities knew it would distract from the violence they enacted.3 The attempted genocide that followed included confining Indigenous peoples to reserves, apprehending and abusing generations of children through the residential school system and, in Canada, the “60’s Scoop,” prohibiting cultural engagement, non-consensual medical experimentation, and legislation that continues to disproportionately inflate Indigenous rates of poverty, homelessness, unemployment, and murder. Furthermore, mainstream addiction treatment approaches substance use through a Western world-view, erasing traditional knowledge systems and perpetuating colonial disruption.

    Is it any wonder, then, that Indigenous people are more “prone” to substance use?

    This is not to say that personal stories aren’t unique, or that individual trajectories won’t be informed by multiple, intersecting forces throughout the life course. We can’t accurately predict behavioural outcomes based on one or two bits of demographic information, but we can (we must) analyze trends (addiction-related and otherwise) within their historical contexts.

    Initially, I was fascinated by this information but didn’t think that it applied to me. I was raised in a wealthy suburb. I’m White. I had been sexually harassed, sure (and raped multiple times while homeless), but every AA sponsor I’d had told me this was further evidence of my powerlessness over substance use. “We put ourselves in vulnerable positions while using—when you stay sober, you’ll stop being taken advantage of.” My life chances hadn’t been constrained by systemic oppression (other than ableism, but I did not yet identify as neurodivergent), just my own bad choices, so I remained convinced that while addiction is beyond some, less privileged, people’s control, the origins of my own usage still lay firmly within me.

    Then I learned about trauma. My professors introduced me to the implications of interpersonal trauma, and they demonstrated that prolonged developmental trauma, regardless of perceived severity, fundamentally alters one’s nervous system.2 I won’t disclose intimate details of my childhood, but I will say that one needn’t be raised in poverty or contend with racism to regularly feel afraid. This can have enormous physiological consequences in childhood, as being in “fight or flight” mode can lead to mood disturbances4, emotional dysregulation5, and loss of connection6—all potential roots of addiction.

    Over time, it became evident that personal traumas are inextricable from broader (“macro-level”) structures such as the economic system. Our “micro-level” communication is shaped by the norms and expectations of society, so values such as individualism, a product of capitalism, invariably affect our actions. AA itself is hyper-individualized: It treats addiction as a “spiritual malady,” and in so doing it mars one’s ability to interrogate how social inequalities (and the maladaptation they evoke) make substance use desirable—and sometimes very necessary.

    With this, I questioned everything.

    “What if I had been raised differently because my parents had been raised differently? If my Grandparents hadn’t been impoverished immigrants, would we all have been a bit more inclined toward tenderness? Would I still have developed an eating disorder?”

    “What if I developed an eating disorder, but the response to it had been less informed by a lineage of poverty? Rather than see bulimia as indulgent, would my parents have had the skills to inquire about the feelings underneath? Would I still have started drinking?”

    What if, when I started drinking, I hadn’t been sent to addiction treatment that taught me that sickness was innate? Would I still have blamed myself for all that had happened, prompting an endless cycle of institutionalization, homelessness, self-flagellation via health-negating behaviours, subsequent institutionalization, and even fiercer destruction each time it didn’t have the desired result?

    On and on and on. But, most importantly:

    “Wait. Why is high-intensity alcohol and illicit drug even considered bad in the first place?”

    I specialized in the medicalization of deviance (“abnormality”) as a mechanism of social control.7 In so doing, I catapulted head-first into a voyage of unlearning everything I knew about addiction. I was enabled in part by research, yes, but mostly grew from a) leaving AA and figuring out who the hell I was beneath the meetings and the chanting; and b) connecting with drug user activists. They, more-so than any text, instilled in me that the war on drugs, not drugs themselves, is a threat to our survival.

    The history of alcohol and drug prohibition has been thoroughly documented elsewhere, so I needn’t repeat it here. Suffice to say that some substances are illegal not due to their chemical properties, but because they used to afford racialized immigrants and descendants of slavery economic and festive alternatives to wage labour. This threatened colonial nation-building projects, so state officials criminalized anything that might undermine their access to a compliant, exploitable workforce. Substance use also triggered fears of racial mixing (a major no-no among White European settlers obsessed with racial purity), and it threatened Victorian-era morality because ultimately, getting high feels really fucking good.

    Today, the “disease model of addiction” has been naturalized in common discourse. That frequent, high-intensity substance use is a “chronic, relapsing condition” is a taken-for-granted assumption, with few publicly questioning why so many of us get and stay afflicted.

    But, when we closely examine the most damaging outcomes of addiction—unemployment, incarceration, lack of access to medical treatment, homelessness, fatal overdose, suicide—we see that most are derived from the stigma, discrimination, and legislation surrounding use, not the actual act of using.

    If, for example, heroin were to be publicly available, regulated, and normalized, people wouldn’t have to use in secret. They would know exactly what and how much they were getting instead of being poisoned by a toxic drug supply, and this would substantially reduce one’s risk of overdose. Beyond this, not getting fired or acquiring a criminal record by using would enhance employment options, and homelessness due to “unemployability” would thus be less prevalent.

    Additionally, sustained illicit use necessarily propels one into a nefarious shadow world, one in which using becomes priority and social norms are suspended in favour of acquiring one’s next fix. How much of deviance is the result of not caring to participate in society, and how much is learning to not care after being treated like a degenerate? We internalize the labels ascribed to us, and we begin to act accordingly.

    So where does this leave me?

    Blue banner featuring an image of the book The Becoming by Nicole Luongo

    Ultimately, I have come to see my own alcohol and crack-fueled binges, which now happen roughly once every 12 – 18 months, as the culmination of economic, political, legislative, institutional, and inter-personal failures. When I have tried to prevent benders by seeking help for post-traumatic stress (and the terrifying dissociative and somatic symptoms that accompany it), my first option is a sterile psychiatric ward, where I exist behind locked doors, am medicated beyond recognition, and am released with an appointment slip reminding me that a month later I am to meet with a harried psychiatrist who will review my medical records, tell me to consider permanent institutionalization, and prescribe me sufficient doses of antipsychotic and mood-stabilizing drugs to kill myself should I opt to (which I always seriously consider).

    Mid-bender, trying to seek support looks like presenting at an emergency room, waiting for hours while hallucinating or in severe withdrawal, being given hefty doses of diazapam with the instruction not to ingest while drinking (ha!), and continuing to use. My roommates don’t know how to cope, I invariably lose my housing and employment, and those I should be able to call for help have been told by well-intentioned but misguided acquaintances that offering shelter, food, and safety is “enabling” my addiction (for the record, it is not).

    I am left to fend for myself, and after four or so weeks of this I am so depleted and ashamed that I crawl into detox (after a bed becomes available, which can easily take weeks). Afterward, I’m still broke, alienated, and I have nowhere to go.

    When I went to addiction treatment for the final time, I thought that perhaps my experience would be different. I was going of my own volition, I hadn’t just been scraped off the street, and I was optimistic that I might receive the trauma care that I still desperately need. Instead, I watched horrifically abused women be blamed for their condition, and as I felt myself deteriorate, I got the hell out of dodge.

    I am not broken. The system is.

    In some ways, medical sociology ruined me. I can no longer cope with the cognitive dissonance of sitting in twelve-step meetings while people discuss their “selfishness” and “self-centeredness” (the true etiology of addiction, according to the Big Book) while all I see are oppression and bad policy. I’ve tried many times over the years, and each meeting I attend reinforces that these are not, nor have they ever been, my people.

    I also no longer pray to accept the thing I cannot change. I work (even as I oft question whether doing so is useful) to change that which I cannot—will not—accept. The former was easier, but given what I know, being passive in the face of injustice is not a viable option

    I am still recovering.

    By working with other user-activists on drug policy reform, I am recovering from loneliness and despair.

    By supporting a homeless encampment, I am recovering from isolation and political impotence.

    By writing, I am recovering from years of capitalist-induced performativity and my realities being denied.

    According to AA, I am delusional. I most certainly will die soon. To this I say, maybe, but at least I’ll have died not hating myself.

    I also refuse to invite people into my life whose love for me is conditional, so when (not if—when) I use again, I will not be alone. This fills me with great comfort, and it is now more important than a sobriety date ever was.

    I dare call it spirituality.


    Notes

    Please note that I’m not claiming that trauma is the sole cause of addiction, which would be as reductive and deterministic as the program I malign. I broadly define trauma as structural violence, symbolic violence, and the more obvious interpersonal troubles it induces. With a background in medical sociology, I have been trained to minimize biological contributions to addiction; but severe, sustained use (which is more prevalent in marginalized groups), leads to physiological adaptations that make reducing or stopping one’s use more difficult.

    I fully believe that some people (most people, actually) can transition away from problematic use and learn to use moderately. I am not one of those people.

    I don’t wish to dispute that sustained substance use can have deleterious mental and physical health outcomes. As someone who narrowly evades death semi-regularly, it absolutely can. Still, I maintain that this is mostly a result of policy and stigma.

    References

    1. Mills, C. W. (1961). The sociological imagination. New York, NY: Grove Press
    2. 2. van der Kolk, B. A. (2014). The Body Keeps the Score: Brain, Mind, and Body in the Healing of Trauma. (pp. 99)New York, NY: US: Viking
    3. Frank, J. W., Moore, R. S., & Ames, G. M. (2000). Historical and cultural roots of drinking problems among American Indians. American Journal of Public Health, 90(3), 344–351.
    4. Lanius, R., & Olff, M. (2017). The neurobiology of PTSD. European Journal of Psychotraumatology, 8(1), 1314165
    5. Hopper, J. W., Frewen, P. A., Kolk, B. A. V. D., & Lanius, R. A. (2007). Neural correlates of reexperiencing avoidance, and dissociation in PTSD: Symptom dimension and emotion dysregulation in response to script-driven trauma imagery. Journal of Traumatic Stress, 20(5), 713 — 725. doi: 10.1002/jts.20284
    6. Sherin, J. E., & Nemeroff, C. B. (2011). Post-traumatic stress disorder: The neurobiological impact of psychological trauma. Dialogues in Clinical Neuroscience, 13(3), 263 — 278.
    7. Conrad, P. (1992). Medicalization and social control. Annual Review of Sociology, 18(1), 209–232. doi: 10.1146/annurev.so.18.080192.00123

  • Moms Stop the Harm and Lethbridge Overdose Prevention Society Launch Legal Action Against Alberta Government

    Moms Stop the Harm and Lethbridge Overdose Prevention Society Launch Legal Action Against Alberta Government

    supervised consumption service lawsuit in Alberta supervised consumption service lawsuit in Alberta

    The Government of Alberta is threatening the health and safety of people who use drugs by rolling back reforms introduced by the federal Liberals in 2017 and imposing additional barriers to accessing supervised consumption services. The Liberal reforms in 2017 made it easier to set up harm reduction services in the province. The Government of Alberta has now introduced onerous requirements to service providers and service users that will make it more difficult to access and provide life-saving care.

    These requirements include the following:

    • Providing a name and personal identifying information to access service
    • Good Neighbourhood agreements that far exceed current consultation requirements that make it virtually impossible to open any new harm reduction sites or renew existing ones
    • Standards for staff qualification and training that will exclude many people with lived and living experience
    • Onerous reporting requirements that are impossible for grassroots organizations, often operating out of a tent, to operate
    • High fines for non-compliance that will bankrupt small agencies

    In response, Moms Stop the Harm and the Lethbridge Overdose Prevention Society (LOPS) have commenced legal action against the Government of Alberta to ensure that no additional barriers to access and provision of life-saving supervised consumption services are introduced.

    “We know that our children would not have died had their overdoses taken place at a consumption site. This option was not available to them at the time. We also know how stigma and shame made them hide their use. We strongly oppose the new provincial guidelines as they will create barriers that will keep people from life-saving services. We know how hard it is to grieve someone you love and every overdose reversed is a family that does not need to arrange a funeral. This is why we launched this lawsuit together with LOPS—to save lives and to give people hope for the future.”

    Kym Porter and Petra Schulz, Moms Stop the Harm

    Both organizations argue that these changes—introduced in “Guidelines” by the Government of Alberta—conflict with the federal government’s goal of improving access to harm reduction services in 2017. They also allege that the Guidelines breach sections 2(a), 2(b), 7, 8, 12, and 15 of the Charter of Rights and Freedoms.

  • We grieve for the communities of the 215 Indigenous children

    We grieve for the communities of the 215 Indigenous children

    This past week laid bare the dark history of Canada’s colonial past: 215 bodies of Indigenous children were uncovered on the grounds of a former residential school in Kamloops, British Columbia, on the territory of the Tk’emlúps te Secwépemc peoples. The horrific realities seized even the attention of the international media and government flags have been lowered to mark the tragic discovery.

    We take pause in our work on drug policy in Canada to once again remember that our current drug policies have colonial and racist roots and that our work ahead is to stand with and support Indigenous Peoples and work together to create policies that end the discrimination, oppression and other devastating consequences so many experience.

    The discovery of these unmarked graves makes clear what Canadians must acknowledge: that Canada is founded on and continues to operate through colonial, systemically racist systems that continue to cause significant harm to Indigenous communities. Make no mistake, this was genocide. Grand Chief Stewart Phillip, of the Union of British Columbia Indian Chiefs, said to the media,

    “This is the reality of the genocide that was, and is, inflicted upon us as Indigenous Peoples by the colonial state. Today we honour the lives of those children, and hold prayers that they, and their families may finally be at peace.”

    The memory of this atrocity and commitment to reconciliation must not fade with the passage of time; and governments must step up and fully commit to justice for and self-determination of Indigenous communities.
    As a coalition committed to transforming Canada’s drug policies to those that support and empower Indigenous Peoples, we are committed to working with Indigenous organizations to dismantle a drug policy framework that has had such devastating impacts.

    At this time, we encourage you to support Indigenous organizations working towards transformation and healing for the survivors of residential schools and ask you to consider donating to the Indian Residential School Survivor Society, an organization that has been providing support for survivors for over 20 years in British Columbia.

    Memorial on the steps of the BC Legislature; Victoria; 2021

    Along with voicing support and outrage on social media, we can write to our Members of Parliament and show our commitment by supporting Indigenous-led organizations who are best positioned to provide healing during this traumatic time.

    Let this not be a flashpoint moment that dims with the next “big news story,” and let us become even more committed to having difficult conversations with our friends and families about what it means to truly seek reconciliation. Silence and apathy must end here as we move towards justice for and reconciliation with Indigenous communities across Canada.

  • Cycling to stop the harm. A journey across Canada in support of progressive drug policy

    Cycling to stop the harm. A journey across Canada in support of progressive drug policy

    iliajah pidskalny cycle iliajah pidskalny cycle iliajah pidskalny cycle iliajah pidskalny cycle iliajah pidskalny cycle iliajah pidskalny cycle iliajah pidskalny cycle

    On January 1, 2021, I hopped on my bicycle and rode from Saskatoon to Vancouver on a project called Cycle to Stop the Harm, to raise awareness around the drug poisoning crisis, drug policy reform, and mental health. Along with awareness and outreach, I raised money for Moms Stop The Harm and the Canadian Drug Policy Coalition—two amazing groups among many working at the leading edge of drug policy reform, outreach, and education. Full of determination, I left with a fundraising goal of $20,000 and a bicycle packed with everything I needed to survive winter camping and cycling from the prairies, through the mountains, and to the west coast. After 29 days and roughly 1670 kilometres, I successfully arrived in Vancouver with all my toes and fingers on January 29, 2021 with a total of $25,450 raised. Above all, this meant a voice for tens of thousands of people who are otherwise unheard and a chance to raise awareness around the current drug poisoning epidemic.

    Iliajah Pidskalny; 2021

    During that month, I received many questions: Why bicycle? Why winter? Why during a pandemic? What did you eat? Why peanut butter? What motivated you when it was most challenging? What was your training like? What will you do afterwards? Is there a personal connection to this issue? And the most common and most important question: what harm are you referring to?

    The simple response to the latter is the harm done by our current drug policies, which have been a failed model for decades. The “war on drugs” is a useful term as it emphasizes the aggression of our current approach which, like war, costs a lot of money and many lives. After decades of failure, this model contradicts evidence, logic and human rights. The drug poisoning crisis is a manifestation of the harm caused by the war on drugs and is a serious epidemic taking the lives of thousands of people.

    Is there a personal connection?

    No, I do not have a personal connection to overdose nor fentanyl poisoning. However, I am a human, and so I have a personal connection to other humans. I am embarrassed about this pitiful and devastating “war on drugs,” the policies of which are illogical and unjust. The policies have been justified by miseducation around drugs, drug use, and mental health, which has created a culture of stigma and accepted marginalization. Canada should take this issue more seriously before every Canadian has lost a loved one to fentanyl poisoning or overdose. There is no “us and them.” Taking a more empathetic and human rights approach to drug policies will not only expose systemic inequalities—whether socioeconomical, cultural, racial, or gender-based—it will also help us better understand mental health.

    So when asked, “What harm are you referring to?”

    I was ultimately referring to the harm caused by our own mind. Whether we’ve lost a loved one or are genetically prone to depression, our mind is at the root of so much suffering. Cycle to Stop the Harm was about mental health. Drug policy reform is the perfect place to increase research, understanding, and compassion regarding mental health and to decrease stigma (not to mention save tens of thousands of lives). Whether it’s depression, loneliness, anxiety, addiction, greed, hatred, or jealousy, we are all susceptible to mental and emotional ailments. That is the essence of why I began Cycle to Stop the Harm. That is why I was so motivated to bring awareness to this issue even if it meant the constant threat of hypothermia and frostbite for 29 days. I was riding for every boy and girl lost to fentanyl poisoning and for every mother and father who now suffers from their loss. I was riding for impoverished communities in Canada, Ghana, Mexico and every other country. I was riding for the rich and the poor, the religious and the atheist, the young and the old. Each day on that bicycle, I rode for every individual human.

    Why bicycle?

    I knew that I could bicycle and camp in the winter. I knew that a crazy journey like this could get some attention. I knew that I could give a voice to so many people who don’t have the opportunity/resources to speak up (or be heard).

    Saskatchewan highway; 2021

    Why winter?

    I got the idea mid-December and I was not willing to wait. People say I’m impatient, but I call it enthusiastic. I also knew my journey would gain much more attention in winter than in summer. Furthermore, riding and camping in the winter highlights some (and only some) of the challenges experienced by Canadians who are homeless. After witnessing homelessness during another six-week winter bicycle journey in eastern Canada (October 23 – December 3, 2020), I wanted people to rethink the challenges of homelessness. I often wondered why people would call me adventurous or brave, yet rarely said anything like that (or anything at all) to people who live on the streets. Living outside in the winter sucks, even if you have good gear and do it by choice. I can’t imagine what it’s like involuntarily living without shelter and struggling with other barriers, including severe mental illness and stigma.

    Why during a pandemic?

    Although the world’s in the grips of a tragic pandemic, homelessness, addiction, depression, suicide, mental illnesses, and social inequalities don’t stop. In fact, overdose and suicide have only gone up in many communities during this time. For me personally, I wasn’t going to wait until the pandemic was “over” until I cared about these issues. I followed all pandemic protocols and was willing to take the extra challenges involved, which meant living/cycling for two weeks in a tent by myself until I could be hosted in a home. That totalled two warm homes in the month of January, and not nearly enough showering…

    As for the journey itself, I’ll try to summarize some of the challenges.

    Thanks to good gear, I was never cold during the night. However, every morning I had to crawl out of my warm sleeping bag and put on frozen socks, frozen boots, and frozen mitts. Overnight, my breath would precipitate as snow on the inside walls of my tent. This meant that any sudden movement, it would be snowing in my tent. I had spare dry socks, but my boots were wet (frozen), so I saved them for emergency (which was never, thankfully). Day after day, everything got more wet and more frozen.

    Camping along Cycle to Stop the Harm route; 2021

    After I put my frozen socks and mitts on, I would then pack up camp in the dark so that I could ride at dawn. Since I had limited daylight (especially in the beginning), I would cycle from dawn to dusk. It took a lot of time and energy to make and pack up a good winter camp everyday. I had to bicycle at least 80 km a day for it to be worthwhile. Riding 80 km was tough against prairie headwinds (consistently 50 km/hr and sometimes gusting up to 90 km/hr), but in the mountains I started averaging 120 km a day.

    Once camp was packed up and the bike was ready to go, one of the hardest parts was next: shedding some layers before cycling. That always sucked. Singing and talking hysterically seemed to help. It was just a matter of cycling hard until my body would generate enough heat such that the involuntary and lifesaving shivers would stop. But, before that moment, the bitter cold seemed to desperately draw physical and mental energy out of me… day after day. Once I was fully warmed up, I cycled with only a long sleeve shirt, thin polyester leggings, and swimming trunks. Then to the next hardest part: stopping for a break. If I stopped, I would get extremely cold, shivering and teeth chattering within a few minutes (or sometimes seconds). Standing in middle-of-nowhere Canada with a shiver like that is a quick trip to severe hypothermia. My only source of heat was my body via exercise. So, I would rarely stop and only briefly. A quick sip of water (which had to be stored in a thermos) and a quick handful of as many calories as possible before cycling again. I noticed that bicycling with a mouthful of food, trying not to choke and wearing a face mask all at once was a quick way to warm up after a break.

    What did I eat?

    Each morning and evening I ate rice noodles with peanut butter. But to sustain me for the rest of the day, I would make energy bars from dates, chocolate, peanut butter and tortilla chips. After cycling all day, I would always get a nasty chill when I finally stopped riding in the evening. The only way to shake the chill was to set up camp as fast as I could (which worked surprisingly well every time). Then I would cook my rice noodles for dinner, often with vegetable juice or canned tomatoes and of course, peanut butter. I ate other things along the journey, especially candy in Saskatchewan and potato chips in Alberta. But, once I learned that the combination of dates, chocolate, peanut butter, and tortilla chips made me feel invincible, I never looked back. And so it was, for 29 days.

    Eating a meal during Cycle to Stop the Harm; 2021

    Why peanut butter?

    For those who had followed the journey on social media, they noticed a consistent theme of peanut butter. It was in part a joke, but also the majority of my caloric intake. This is because it is cheap, but also because I have some serious gut health issues (IBS). My health issues have almost convinced me to stop travelling and doing adventures like this, but I’ve decided instead to adjust my lifestyle (diet) in a way that allows me to do the things that I love most. Of course, I’ve had to redefine what it is that I love most; but that, combined with peanut butter allows me to push on. (I share this to help remind people that I’m human, and to not over-romanticize my character qualities).

    What motivated me when it was most challenging?

    I met many people along the journey and everyone had a story—whether it was losing a friend to fentanyl poisoning or their own story about alcoholism, using heroin, or addictive shopping. Everyday, I would be reminded about who and what I was riding for: everyone and their mental health. When my toes were numb or the headwinds were gusting 90 km/hr, I just had to remind myself, “This isn’t about you, Iliajah. This is about everyone, including you.” I would look up at the mountains and think, “Be patient like the mountains, strong like the wind, and humble like the dust.”

    During the month, I rarely thought about my final destination. Instead, I focused on one day at a time. Cycling and camping in the cold requires a lot of focus, and there was little time for me to celebrate or relax. Every minute was highly calculated, as I constantly danced with the threat of hypothermia and frostbite. However, when I left Manning Park at -20C one morning and arrived in Agassiz at +8C the same afternoon, I felt an overwhelming sense of relief. At that moment, I knew that I had successfully completed the journey and that I would safely arrive to Vancouver in only a few more days. By the time I arrived at my official final destination, Jack Poole Plaza (at the Olympic Flame) in Vancouver, I only felt an inexplicable exhaustion from my journey and an excitement for what lay next.

    Jack Poole Plaza; Vancouver; 2021

    What was my training like?

    I spent the last six years without a vehicle, which meant many winters and many long distance bicycle rides. My first journey was from Saskatoon to Vancouver (in the summertime when I was 18 and with a buddy), and I fell in love with long distance cycling. Since then, I’ve done long hauls in Indonesia, Cambodia, Spain, and others in Canada. My legs were ready for Cycle to Stop the Harm. However, winter is a different beast and so this time my training was focused on my mind. I’ve been lucky enough to have the time, energy, and resources (books, wifi, people) to have stumbled upon and practiced meditation. This was the key to the empathy and compassion that motivated me to embark on a bicycle journey in the dead of winter for no one in particular, yet every particular person.

    What did I do afterwards?

    I went to Vancouver Island and continued to bicycle for Cycle to Stop the Harm. I had closed the fundraiser and decided to focus on conversation and reducing stigma. I thought it would be a more relaxed version of my month in January, but I was very wrong. It was another month full of numb hands and feet, with wet shivering and teeth chattering battles against hypothermia. It was far more challenging than the first month because there was no endpoint. Less people were paying attention, and so my life threatening efforts felt pointless. Alas, I rode another ~500 km from Nanaimo to Campbell River, then south to Victoria, and then finally back to Nanaimo. The project ‘Cycle to Stop the Harm’ has since been put to rest, while I take some time to heal and stop harming my aching body. But, as the days get warmer and the sun shines longer, I can smell ideas blooming in my mind. The next project awaits, and will blossom when the time is right.

    With love and enthusiasm
    Iliajah Pidskalny

  • Looking ahead to 2021 and the fight for drug policy reform

    Looking ahead to 2021 and the fight for drug policy reform

    canadian drug policy coalition 2021 canadian drug policy coalition 2021

    There’s no denying that 2020 was a disaster. The human toll can be expressed in numbers, but the impact and actual loss is incalculable. Friends, family, lovers and co-workers died—many alone, and most from failed drug policy. 

    Though many of us understandably want to forget about this past year, we must not overlook the courage, ingenuity, and determination that helped move the dial on public health, harm reduction, and drug policy. COVID-19 helped the public see and understand the dire health inequities plaguing Canadian society. Supervised consumption, decriminalization of drugs, and safe supply entered public discourse and consciousness in a way they hadn’t in the past. This was due to the work of frontline advocates and communities affected by the harms of prohibition.

    A mourner sits on the ground at a rally in Vancouver
    International Overdose Awareness Day; Vancouver; 2020

    Not only did the overdose epidemic continue to rage in 2020, but the addition of the COVID-19 pandemic meant that Canadians were isolated from their regular supports. COVID-19 may have finally brought some folks shelter, but it also came with an increased risk of overdose because these individuals were now living alone. 

    Looking forward, there is an enormous amount of work to be done in 2021. The illegal drug market is still tainted with poisoned drugs. Stigma and discrimination still push people into the shadows. Municipal and provincial governments continue to deny the evidence of harm reduction and its positive impacts. We must keep the pressure on as we endeavor to change the minds of our elected leaders and convince them to support progressive drug policy. 

    In 2021, the Canadian Drug Policy Coalition will train its focus on decriminalization and the legal regulation of drugs to help end the harms of the toxic drug market. We will do this through a range of major projects, each with its own audience and goal to push Canada towards a future free from drug policy-related harm.

    Rally in support of Lethbridge Overdose Prevention Site; Lethbridge, AB; 2020

    At the frontend of our efforts is, Getting to Tomorrow: Ending the Overdose Crisis, a national public health dialogue project aimed at helping Canadians realize that we all share the same goals: a safe and secure society free from the harms of a toxic drug supply. The project will bring together community leaders across Canada to identify shared values, goals, and a collective vision for change so that Canadians can work together towards solutions. Getting to Tomorrow aims to bridge the divide within communities that so often stands in the way of life-saving progress and build a broad base of public support that will help animate our other major initiatives and efforts.

    Broken Drug Policies is a similar project focused in British Columbia hoping to leverage the gains in drug policy, already introduced at a provincial level, to accelerate drug policy reform. Broken Drug Policies will help the public understand how interconnected systems (health care, criminal justice, social services, employment) drive substance use and the power they as citizens have in influencing those systems to create change. 

    The Regulation Project will do a deeper dive into what a system of legal regulation of drugs could look like. Ultimately, it is only through a safer and regulated supply of drugs that the scourge of overdose deaths can end, and envisioning this future free from harm is a vital first step. As part of the project, CDPC will be consulting key stakeholders—principle among them people who use drugs—on what factors would ensure that a system of legal regulation would succeed. How would people access safer drugs? Who would have access to them? When and where could they these substances be obtained? All these questions will be explored to lay the blueprint for life-saving change.

    Two men carry a large black wooden coffin along the march route
    Vancouver Area Network of Drug Users Memorial March; Vancouver; 2020

    Working alongside this effort is Imagine Safe Supply, which seeks to clearly articulate the concept of “safe supply” and what it means for those most directly impacted by the harms of our current drug policy: people who use drugs. Having a clear and accurate understanding of this concept is the necessary foundation for transformative policy.

    With the rollout of COVID-19 vaccines we are happy to begin planning of Stimulus 2022: Drugs, Policy and Practice in Canada, the country’s largest harm reduction and drug policy conference that will bring together harm reductionists, people who use drugs, government, community leaders, advocates and academics to share knowledge and build community and capacity to better respond to the worst overdose crisis in Canadian history. 

    As we look to 2021, we look with hope. We need to come together now more than ever as we walk this tremendous path to change failed drug policies and save lives. We hope that you’ll walk alongside us.

  • Canada’s busiest supervised consumption site shuts its doors on International Overdose Awareness Day

    Canada’s busiest supervised consumption site shuts its doors on International Overdose Awareness Day

    ARCHES closes on international overdose awareness day, ARCHES closes on international overdose awareness day

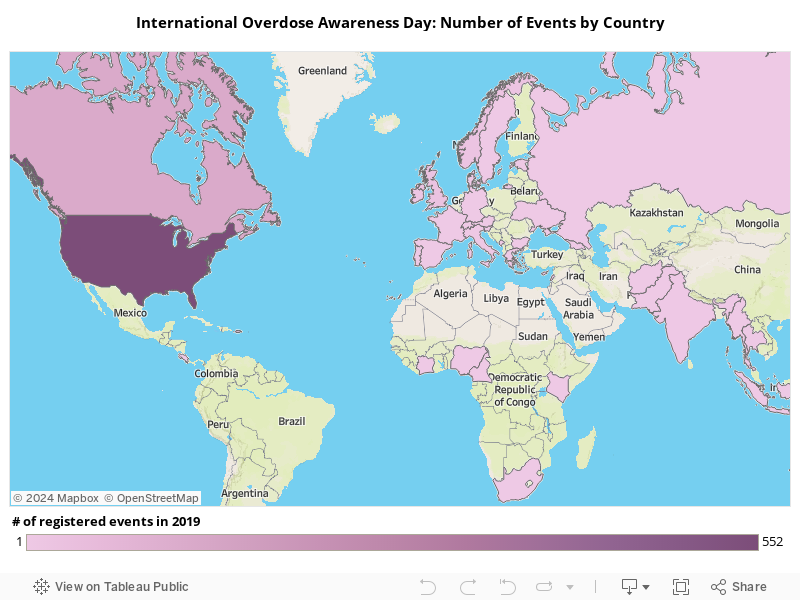
    International Overdose Awareness Day began in Australia in 2001 as a bold and public call to combat stigma around drug use, honour the lives that have been lost to overdose, and educate society on the life-saving value of harm reduction. It has grown every year, with a record 874 global events and participation from 39 countries, including Canada, in 2019. These are all encouraging signs that society is waking up to (and communities are mobilizing around) the truth that drug prohibition has failed and a new human rights- and public health-based approach to drug policy is desperately needed. 

    (Interactive)

    But it’s hard to sense this shift from the actions of the Alberta government, which recently cut funding to Canada’s busiest supervised consumption site, ARCHES, which forced its closure. The doors close today, International Overdose Awareness Day—a time when we should be moving towards progress through compassionate, evidence-based drug policy by embracing more harm reduction, not less. Instead, Alberta, in darkly ironic fashion, is sliding backwards—a regress that erodes the public health and safety of one of Canada’s hardest hit provinces when it comes to overdoses.

    Since opening in March of 2018, ARCHES, located in Lethbridge, Alberta, saw an average 663 visits per day. “That’s more daily visits than the busiest sites in Toronto—a city of more than two million, and Vancouver—where Canada’s first supervised consumption site was founded in 2003,” according to the Star Edmonton. The number of lives saved and positive impact to the greater community is immeasurable, so it is both baffling and dangerous to shut the doors on such a vital health service. Research from chief coroners across Canada makes it clear that using drugs alone is extremely risky at a time when the drug market is so toxic. People will likely die without the supervised consumption services ARCHES provides and the supportive environment it affords.

    In the first quarter of 2020, there were 127 fatal overdoses related to fentanyl in Alberta, an increase from the previous quarter where there were 105. 85% of the deaths this year occurred in larger urban centres like Edmonton, Calgary, Red Deer, and yes, Lethbridge1.

    In such a climate of death and human suffering, governments should be expanding harm reduction, not scaling it back. Alberta’s provincial government decided to pull funding after a financial audit found suspected financial irregularities around spending and expenses. But this is no reason to punish the marginalized clients who use the facility daily—whose very lives depend on its services and the community of care that has formed around them.

    TAKE ACTION: Sign the open letter to restore funding to ARCHES

    The Government of Alberta announced a mobile site will replace the services lost with the closure of ARCHES. But advocates warn that this can in no way replace the scale of services and community building a site like ARCHES provided. They’ve done the math, and the numbers are a cause for deep concern.

    Across Canada fatal overdoses are climbing, fuelled by the stress and public health strictures of COVID-19. In July, deaths hit a grim milestone in Toronto, claiming more lives than the coronavirus. Saskatchewan recorded more fatal overdoses in the first eight months of this year than all of 2018, “meaning the province may have set a new record for the number of people who have lost their lives to overdoses. The Saskatchewan Coroners Service says there were 40 confirmed and 139 suspected drug toxicity deaths between Jan. 1 and Aug. 6, for a total of 179,” writes Zak Vescera of the Chronicle Herald.

    (Vancouver Area Network of Drug Users memorial march; Vancouver; August 15, 2015)

    And in British Columbia, two consecutive months of record-breaking overdose deaths have both shattered and enraged the spirits of affected communities. This May there were 171 fatal overdoses; in June, 177; and in July, 175. Across Canada, grief, fatigue, and rage surface in equal measure as frontline communities fighting two public health crises (COVID-19 and overdoses) also battle hostile local governments threatening their ability to save lives.

    READ MORE: COVID-19 harm reduction resources

    Now more than ever, International Overdose Awareness Day is needed to affirm the value of harm reduction and the policy changes needed to stem the tide of fatal overdoses: decriminalization and a safe supply of drugs. At a federal level, there is slow and incremental progress. It is not nearly good enough, but better than the backwards direction we’re seeing from a provincial government that seems driven by ideology and out of touch with the science and evidence supporting harm reduction.

    Though drug policy is a federal matter, provincial governments have the power to alleviate some of the harm created by prohibition—which is fuelling overdose death—by, for example, deprioritizing police enforcement of certain drug laws (de facto decriminalization) and choosing where to spend money. Their funding decisions can also create serious harm for affected communities, as will likely be the case in Lethbridge.


    [1] https://open.alberta.ca/dataset/f4b74c38-88cb-41ed-aa6f-32db93c7c391/resource/45e03e51-0fa8-49f8-97aa-06b527f7f42c/download/health-alberta-opioid-response-surveillance-report-2020-q1.pdf

  • Decriminalizing drugs and the path towards defunding police

    Decriminalizing drugs and the path towards defunding police

    With global protests igniting around the killing of George Floyd in Minneapolis, calls to defund police are growing louder. For some, this may seem like an extreme proposition, but as the history of drug policy in Canada and globally has shown, the criminalization of drugs—and millions poured into police budgets to enforce associated laws—have fueled some of the greatest harms to society.

    This interview by Black Lives Matter Toronto co-founder, Sandy Hudson, articulates the clear logic around defunding police and what that means: reallocated funds more intelligently and eliminating from police control those roles they are now performing that cause serious community-level harm, and getting other more capable organizations to carry out those activities. Social development is key to creating healthier and safer communities. We believe it would make society safer by reallocating resources into vital social programs—like housing and employment services—that would do a better job in creating safety for everyone.

    The significant resources pouring into enforcing inhumane drug laws that criminalize the possession of controlled substances for personal use is one of many areas in the purview of police that should be defunded. There is a mountain of evidence showing that criminalizing people who use drugs is extremely harmful. Currently amidst the COVID-19 pandemic, the criminalization of drugs forces people to consume substances in isolation and engage in survival strategies that increase their risk of fatal overdose.

    The millions we spend on criminalizing drug use could instead be funnelled into harm reduction and drug treatment programs that have been proven to save lives and build community, rather than fuel harm. Police themselves have said that they “cannot arrest their way out of the overdose crisis.” The cost in taxpayer dollars, but more importantly human lives, could be reduced by moving away from policing in this area as has been done in other countries.

    (Photo credit: Peter Kim | National Day of Action on the Overdose Crisis | 2018)

    BC’s chief medical health officer, Dr. Bonnie Henry, recently lauded for her pandemic response by the New York Times, has called for the decriminalization of drugs. And this policy shift has been echoed by other leading health experts across Canada. This same shrinking of scope and defunding of budgets is possible in other areas of policing where public health and safety are being adversely impacted by police involvement, such as mental health calls.

    The amazing efforts and courage of Black-led advocacy groups have pushed this issue to the forefront of our collective consciousness at a time when the world is on the cusp of transformative change. In addition to amplifying the messages and calls for change of the #BlackLivesMatter movement, we can play an important role by supporting its efforts on the ground to ensure this pivotal moment in history bends towards justice.

    Please consider donating to Black Lives Matter Toronto or the Black Legal Action Centre to ensure the movement for change continues. 

    Stimulus Connect #3 is happening June 26. RSVP here.

    Drug decriminalization and defunding the police Drug decriminalization and defunding the police Drug decriminalization and defunding the police

  • URGENT APPEAL: Supporting people who use drugs and frontline workers during COVID-19

    URGENT APPEAL: Supporting people who use drugs and frontline workers during COVID-19

    We’re now witnessing two public health crises collide: the devastating COVID-19 pandemic and the unrelenting drug poisoning crisis that is causing so many deaths. Caught in the crosshairs of this unprecedented disaster are people who use drugs and the frontline harm reduction and healthcare workers who support them. Unlike many of us, they do not have the option to stay home and self-isolate, because many may not have a home, and others are performing critical work saving lives each and every day.

    During this time of crisis, let’s help the people saving lives in desperate need of support. We’ve selected five organizations across Canada you can assist through donations of supplies and money. Please give where you can.

    AIDS Saskatoon

    This life-saving organization provides education, advocacy, support and outreach services for people living with and affected by HIV, AIDS and Hepatitis C in central and northern Saskatchewan. Donate here.

    Vancouver Overdose Prevention Society (Vancouver, BC)

    You can donate to the Vancouver Overdose Prevention Society here. The Overdose Prevention Society is in need of thermometers, soap, baby wipes, vitamins, and healthy food.

    Toronto Overdose Prevention Society (Toronto, ON)

    The Toronto Overdose Prevention Society accepts donations through their gofundme link or by direct e-transfer to [email protected]. They are also in need of personal protective equipment (PPE) – gloves, face masks, and hand sanitizer.

    Boyle Street Community Services (Edmonton, AB)

    Since 1971, Boyle Street Community Services has been supporting people experiencing homelessness and poverty in Edmonton. You can donate to them online here.

    Turning Point Society (Red Deer, AB)

    A room with individual stalls

    For over 30 years, Turning Point Society has been responding to the health needs of communities using a harm reduction approach. The organization is in urgent need of masks and hand sanitizer. You can also give online here.

    Other Resources

    The COVID-19 pandemic has brought into sharp relief the flaws in our system of laws and policies around marginalized communities. At this time of crisis, please keep the health and wellbeing of those on the frontlines and individuals without shelter and resources in your hearts. 

    Stay safe, and please give generously where you can.

  • Pain relief that’s a pain in the neck: Issues accessing medicinal cannabis in Australia and Canada

    Pain relief that’s a pain in the neck: Issues accessing medicinal cannabis in Australia and Canada

    I’ve learned very quickly that the Land Down Under and the Great White North have a lot in common: we’re both parliamentary democracies; we’re both partial to smothering french fries in gravy (even if Aussies call them “chips” and don’t add cheese); and of course, we both have universal healthcare.

    Both our countries are understandably proud of our healthcare systems. While witnessing the current heated debate in the United States over universal healthcare, Australians and Canadians alike can find themselves thinking: “oh how primitive, we did that ages ago.” Yet despite our fantastic systems, in both Canada and Australia, patients still struggle to access a vital, all-natural pain relief medicine that has demonstrated a range of other positive health benefits, including helping children with epilepsy reduce their risk of seizure (Thomas & Cunningham, 2019). I am of course talking about cannabis.

    In Canada, medicinal cannabis isn’t a government subsidized medication. This means costs are prohibitively high. In 2019, across Canada the cost of medicinal cannabis per gram was on average 75 cents higher than non-medicinal cannabis. This might seem like a small amount, but when buying in larger quantities to fill a prescription, these costs add up. Medicinal cannabis isn’t subsidized in Australia either; a six- to eight-week course of medicinal cannabis can cost over $750 AUD ($662 CAD). This can cause healthcare costs to rapidly increase; in Australia the cost of treating an epileptic child with a standard dose of medicinal cannabis is $60,000 AUD ($52,573 CAD) a year. Since these costs are not subsidized, this translates into crippling medical bills for a lot of families.

    In response to this, Canada has seen some changes. Organizations like CanniMed subsidize the cost of medicinal cannabis for people on disability or unemployment benefits, and Veterans Affairs Canada also covers registered members for use of medicinal cannabis. Unfortunately, these are the outliers. Large numbers of low-income Canadians in need of medicinal cannabis are still unable to surmount the prohibitive costs.  In Australia, some state governments have sought to surmount financial burdens through compassionate access schemes, such as the framework set up in Victoria under the Access to Medicinal Cannabis Act 2016. This scheme subsidizes the cost of cannabis, but only for children with epilepsy and only if other treatments have failed. Whilst this is an important protection for vulnerable children, the scheme is currently capped at 90 participants, so it too is limited in scope.

    Similarly, both Australia and Canada face issues of “postcode injustice” since there is a far greater degree of access to medicinal cannabis in cities than rural areas. In both countries there are troubling reports of people travelling hours from regional areas to fill prescriptions either due to a lack of clinics altogether or (as occurred in Manitoba in March 2018) clinics running out of stock.

    Of course, the tide is turning in Canada. With cannabis legally regulated for recreational use, doctors are becoming less hesitant to prescribe it. As the normalization of cannabis use continues, insurance companies and government bodies are moving closer towards subsidizing medicinal cannabis. The legal cultivation of cannabis plants also helps bridge the gap for rural communities who might otherwise struggle to access medicinal cannabis.

    Meanwhile, the illegality of cannabis in Australia creates additional barriers to health outcomes, which jeopardizes marginalized people in need of medicine. Whereas wealthy people can overcome the prohibitive costs of accessing pain relief, lower income families are forced to choose between agonizing pain, or the risk of arrest. This is another stark reminder that our outdated approach to drugs has real negative impacts that disproportionately affect disadvantaged groups.

    Australia’s prohibitive regime at least (logically) makes sense: we’re still clutching our collective pearls at the thought of cannabis being used recreationally, so there is accompanying hesitation around its medical use. Despite slow moves to decriminalize recreational use of cannabis in some states and territories, there is still a long way to go before we see widescale legal regulation. But it’s a sad sight that in Canada you can purchase marijuana from a store as easily as you can buy alcohol, yet the medical benefits of this substance are not endorsed by health insurance providers or the government.

    Australians and Canadians have a right to be proud of our healthcare systems. But we shouldn’t forget that when it comes to medicinal cannabis, we’ve got a long way to go. If both countries don’t take greater steps to improving access, our claims of superiority will be little more than blowing smoke.


    Thomas, Rhys H & Cunningham, Mark O (2019). Cannabis and epilepsy. Practical Neurology, 10, 465-471.